Bridge Eastern
and Western
medicine.
TCM Clinical Pro gives integrative practitioners the clinical bridge they need: TCM pattern diagnosis grounded in the classical texts, alongside Western medical correlations, lab recommendations, and specialist referral guidance in one platform.
No credit card required
Western Correlation Generated
Lab tests, referrals & supplements included
30+
Countries served
10+
Treatment modalities
100K+
Diagnoses
4
Report languages
The integrative advantage
TCM precision meets
Western clinical context.
TCM Layer
- Full 4-pillar diagnosis (tongue, pulse, symptoms, emotions)
- Primary + secondary pattern differentiation
- Acupuncture protocol (5 styles)
- Classical herbal formula with modifications
- Cupping, moxa, gua sha, dietary guidance
Western Correlation Layer
- Possible Western differential diagnoses
- Recommended lab tests with rationale
- Imaging studies to consider
- Specialist referral recommendations
- Supplements & nutraceuticals with dosages
Both layers generated simultaneously from a single clinical intake. No switching between tools.
Clinical Synthesis Engine™
Multi-pattern analysis rooted in the classical texts, covering TCM syndromes and functional medicine patterns simultaneously.
Herbal + Supplement Integration
Classical herbal formulas alongside evidence-based supplement recommendations for a complete integrative protocol.
Outcome Monitoring
Track patient progress across 7+ metrics per session, communicate results in both TCM and biomedical language.
Women's & Pediatric Modules
Specialized intake and protocols for gynecology, hormonal health, menopausal care, and pediatric cases.
Multilingual Reports
Generate patient-facing reports in English, Spanish, Portuguese, or French.
Compliance Ready
GDPR and HIPAA-designed infrastructure. Full audit logs and practitioner acknowledgment workflows.
diagnostic hypotheses evaluated per case
Every case is weighed against 250+ diagnostic hypotheses
This is not a lookup table. The Clinical Synthesis Engine™ cross-references your patient's full intake against the differential frameworks documented in the classical canon, then ranks the patterns that actually fit.
4
examinations cross-validated (四诊合参)
360+
acupuncture points with technique rationale
275+
Materia Medica herbs mapped to patterns
Grounded in the classical canon
The engine reasons from the seminal texts of the lineage, not from generic internet data.
Huangdi Neijing
Foundational theory of Zang-Fu and channels
Shanghan Lun
Six-stage differential frameworks
Jingui Yaolue
Classical formulas and internal patterns
Wen Bing Xue
Heat pathology at four levels
How the synthesis works
Structured intake
Symptoms, tongue, pulse, emotions and history are captured as clinical data points.
Hypothesis mapping
Each data point is weighed against 250+ candidate patterns from the classical literature.
Cross-validation
Tongue, pulse and symptoms are checked for consistency, contradictions are flagged, never hidden.
Ranked differential
You receive a confidence-scored differential with the full reasoning displayed for your review.
Every output shows its reasoning. You stay the clinician, the engine does the heavy cross-referencing.
Measured integrative outcomes
Bridging disciplines with measurable impact.
Based on aggregated self-reported data from integrative health practitioners using TCM Clinical Pro:
92%
cross-referencing accuracy
TCM patterns correctly correlated with Western differentials
45 min
saved per intake
Dual-framework assessment generated from single clinical intake
3×
faster lab recommendations
Relevant lab panels identified alongside TCM pattern diagnosis
86%
protocol acceptance rate
Combined TCM + Western protocols used without adjustment
71%
improved interdisciplinary communication
Practitioners report clearer referral letters and shared records
Based on self-reported user data. Individual results may vary. Not a clinical trial.
Inside the platform
Built for real clinical work.
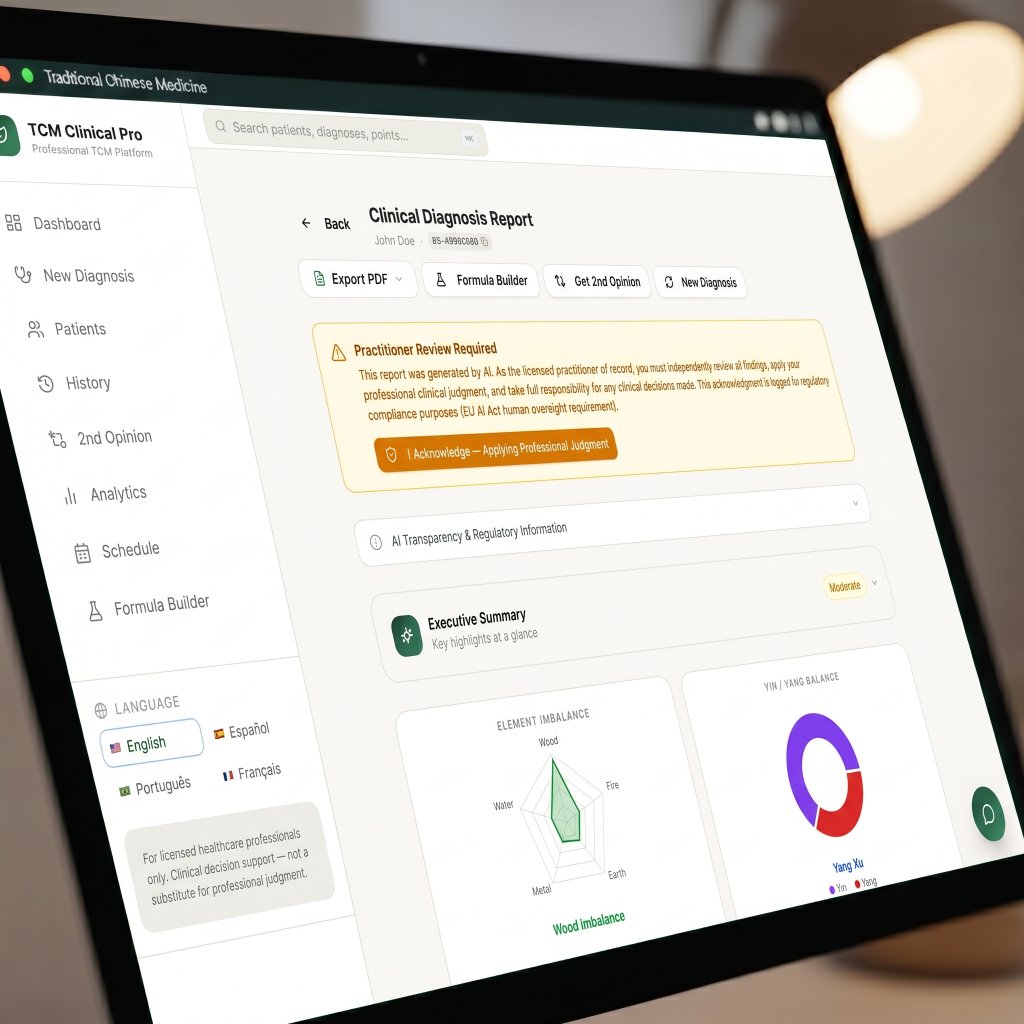
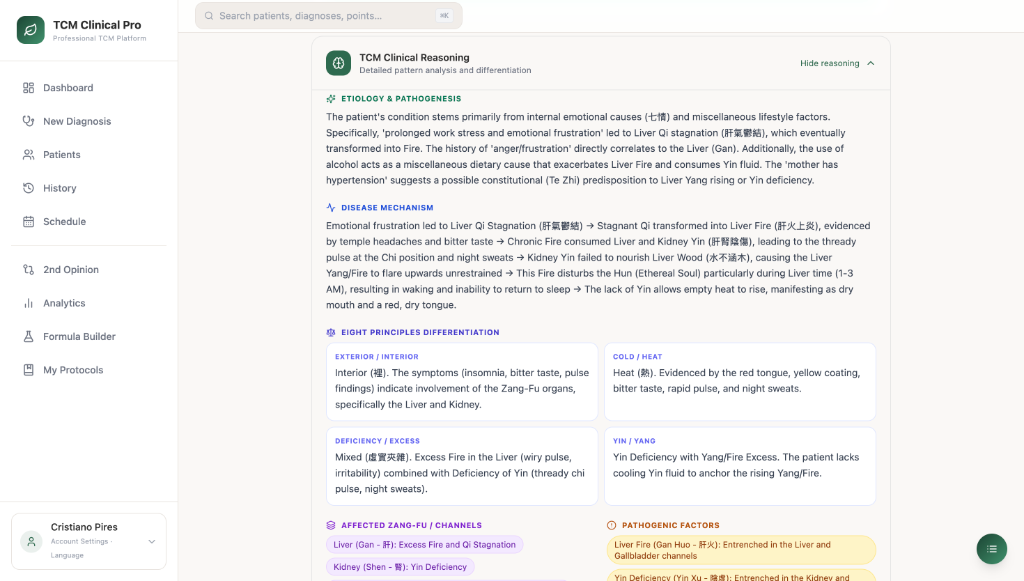
AI pattern diagnosis

Hands-on treatment

Classical herbal formulas

Patient consultation

Tongue & pulse intake
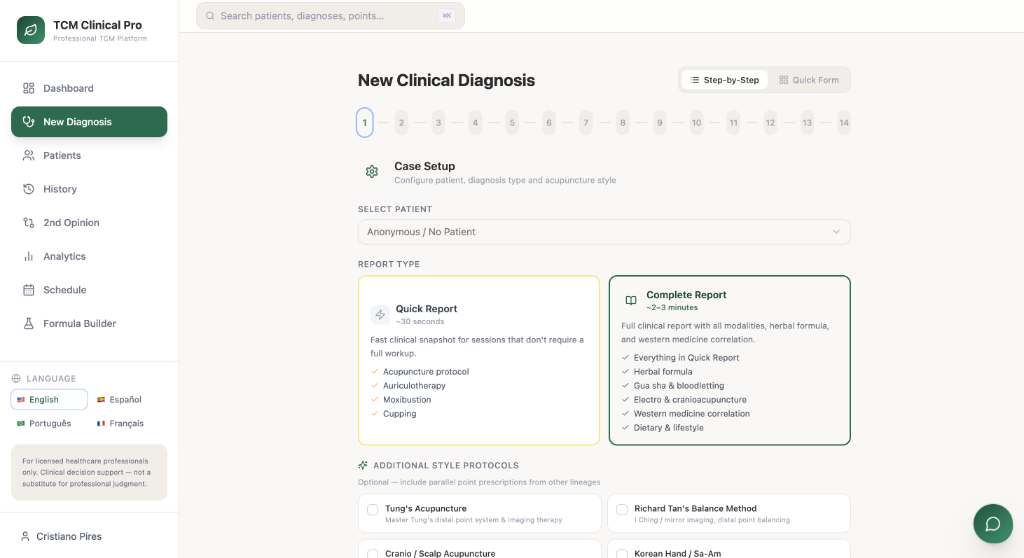
Generated reports
Trusted by US practitioners
What licensed pros across the United States are saying.
"I run a functional medicine practice and finally have a clean bridge between Eastern pattern diagnosis and Western differentials. The dual-language reports make co-management with my acupuncturist effortless."
Dr. Andrew Pearce, MD
Lakeshore Integrative Health, Chicago, IL
15 yrs
"The herbal safety flags catch interactions with my patients' Rx meds before I prescribe. That alone justifies the subscription for our naturopathic clinic."
Dr. Rachel Nguyen, ND
Verdant Health Collective, Seattle, WA
10 yrs
"We've moved away from cookie-cutter protocols. The TCM lens adds a layer my MD colleagues actually engage with, and it's HIPAA-aligned, which my compliance officer signed off on quickly."
Dr. Marcus Brennan, DO
Heartland Functional Medicine, Denver, CO
11 yrs
Names, clinics, and locations shown above are illustrative composites representing typical feedback from US practitioners. Real names withheld to protect client privacy. Individual results vary.
Real Clinical Cases
When labs are 'normal' but the patient isn't, the diagnostic puzzles.
Real cases where Western labs missed the pattern. TCM reveals the functional disorder before it becomes pathology.
Case 1: The 'It's All In Your Head' Patient
38yo Female, 3 years of post-viral fatigue (post-COVID). Brain fog, post-exertional malaise (24–72h crash after any effort), unrefreshing sleep, palpitations on standing, intermittent low-grade fevers. Labs: 'normal' CBC, normal TSH, ANA negative, ESR 18, basic metabolic panel normal. Two specialists dismissed her. Tongue: pale and dusky with red tip, thin yellow coat at root, swollen with teeth marks. Pulse: thin and rapid, weak on both chi, slippery on right guan.
Diagnosis
Lingering Pathogen (Fu Xie) in the Shao Yin layer with Qi and Yin Dual Deficiency, complicated by Damp-Heat smoldering in the Triple Burner and secondary Heart-Kidney Disharmony.
TCM Reasoning
Classic 'Lurking Pathogen' presentation, the original viral pathogen wasn't fully expelled and now hides deep in the Shao Yin layer, emerging episodically (the low-grade fevers and crashes). The combined pale-with-red-tip tongue with rooted yellow coat is pathognomonic. Western labs measure inflammation snapshots, they miss the cyclical emergence. The standing palpitations indicate Heart Qi unable to descend to Kidney; this is functional dysautonomia in TCM terms.
Western Correlation
Long COVID / ME-CFS with probable POTS overlay. Recommended: 10-min standing test (heart rate increase >30 bpm), tilt-table if positive; reactivated viruses panel (EBV, HHV-6, CMV); morning + evening cortisol; NK cell function; mitochondrial markers (organic acids). Refer to Long COVID clinic, but TCM treatment proceeds in parallel.
Treatment
Phase 1 (4 weeks): clear Lurking Pathogen WITHOUT depleting. Sheng Ma Bie Jia Tang modified, lift and disperse, never aggressive purging (PEM trigger). Acu: GV14, BL13, KI3, SP6, short, gentle sessions (15 min). NO electroacupuncture initially (worsens PEM). Phase 2: Tonify with Sheng Mai San + Bu Zhong Yi Qi Tang base. Pacing protocol critical. Mitochondrial support: CoQ10, magnesium glycinate, B-complex. Avoid 'pushing through' fatigue, every crash deepens the pattern.
What to tell the patient
"Imagine an ember hiding deep inside a log, it looks like the fire is out, but every now and then it flares up and burns the whole pile again. Standard tests only check if the flames are visible; they miss the ember. We can't blow on it hard (that's what crashes you), we have to smother it slowly, in layers, until there's nothing left to flare."
Case 2: The Endometriosis Mystery
31yo Female, 9 years of debilitating dysmenorrhea, deep dyspareunia, cyclic GI symptoms (diarrhea premenstrually, constipation mid-cycle), fatigue, low-back pain radiating to right thigh on days 1–2 of cycle. Laparoscopy 2 years ago: 'minimal endometriosis,' surgically removed. Symptoms returned within 8 months. CA-125 normal. Tongue: dusky purple body with purple spots on the sides, sublingual veins distended. Pulse: deep, wiry on both guan, choppy on left chi.
Diagnosis
Severe Blood Stasis (Xue Yu) in the Lower Burner with Cold congealing the Chong and Ren vessels, on a background of Liver Qi Stagnation invading the Spleen, secondary Kidney Yang Deficiency.
TCM Reasoning
The 'minimal endometriosis' label is the trap, the laparoscopy showed minimal visible lesions but the systemic pattern is profound Blood Stasis affecting multiple meridians. The radiating leg pain follows the Liver and Kidney channels through the inner thigh. The cyclic alternation of diarrhea/constipation is Liver invading Spleen oscillating with deficiency. The deep purple tongue and distended sublingual veins indicate this is far more than 'minimal', surgery removed visible lesions but did nothing for the deep stagnation generating them.
Western Correlation
Endometriosis with likely adenomyosis (often missed on laparoscopy) and pelvic floor dysfunction. Recommended: transvaginal ultrasound with deep endometriosis protocol; MRI pelvis with rectal contrast; pelvic floor PT evaluation; consider AMH (ovarian reserve); rule out Hashimoto's (45% comorbidity). Discuss hormonal options with gyn, but TCM addresses the recurrence driver.
Treatment
Days 1–3 of cycle (treat the pain, move stasis): SP10, SP6, LV3, ST29, SP8 (Di Ji, uterine cramping). Strong stimulation. Moxa on lower abdomen + lumbar (CV4, BL23, BL32) days 14–28 (warm Cold, move Blood). Herbs cycle-phased: Days 1–7 Shao Fu Zhu Yu Tang (move stasis, warm cold). Days 8–14 Tao Hong Si Wu Tang (build Blood). Days 15–28 Wen Jing Tang base (warm Chong/Ren, prevent stasis returning). Strict dietary: no cold/raw foods around menses; bone broth + warming spices. Stress management non-negotiable. Realistic timeline: 3 cycles before pattern shifts, 6–9 for stable relief.
What to tell the patient
"Imagine a garden where weeds keep growing back. Surgery pulled the visible weeds, but the soil itself is still feeding them. That's why they returned within months. We're not just cutting weeds this time; we're changing the soil so they can't grow back. You won't see the difference in the first cycle, but by the third the garden looks different."
Start integrating smarter today.
14-day free trial. No credit card. Full access to all integrative features from day one.
🍪 We use cookies
We use cookies to improve your experience and analyse site usage. By continuing, you agree to our Privacy Policy.